Strong current-use field
immunotherapyformyeloma.com
Evidence snapshot
Patients, caregivers, clinicians, and research-aware readers.
Educational only. Treatment depends on cancer subtype, stage, biomarkers, prior therapy, and local approvals.
Patient language access
Multiple Myeloma first, then the full page.
Choose a language to open this multiple myeloma immunotherapy page through Google Translate. Automated translation is for orientation only; clinical decisions still need an oncologist, interpreter, and local treatment advice.
About this cancer
Quick clinical overview
Multiple myeloma is a plasma-cell cancer, usually diagnosed in older adults. It is more common in men and in people of African ancestry.
Related conditions include MGUS, smoldering myeloma, active multiple myeloma, light-chain myeloma, plasmacytoma, plasma-cell leukemia, and AL amyloidosis overlap.
Risk factors include age, family history, African ancestry, MGUS or smoldering myeloma, obesity, immune context, and acquired plasma-cell genetic abnormalities.
Symptoms may include bone pain, fractures, anemia, kidney problems, high calcium, infections, fatigue, neuropathy, or abnormal protein found on blood or urine testing.
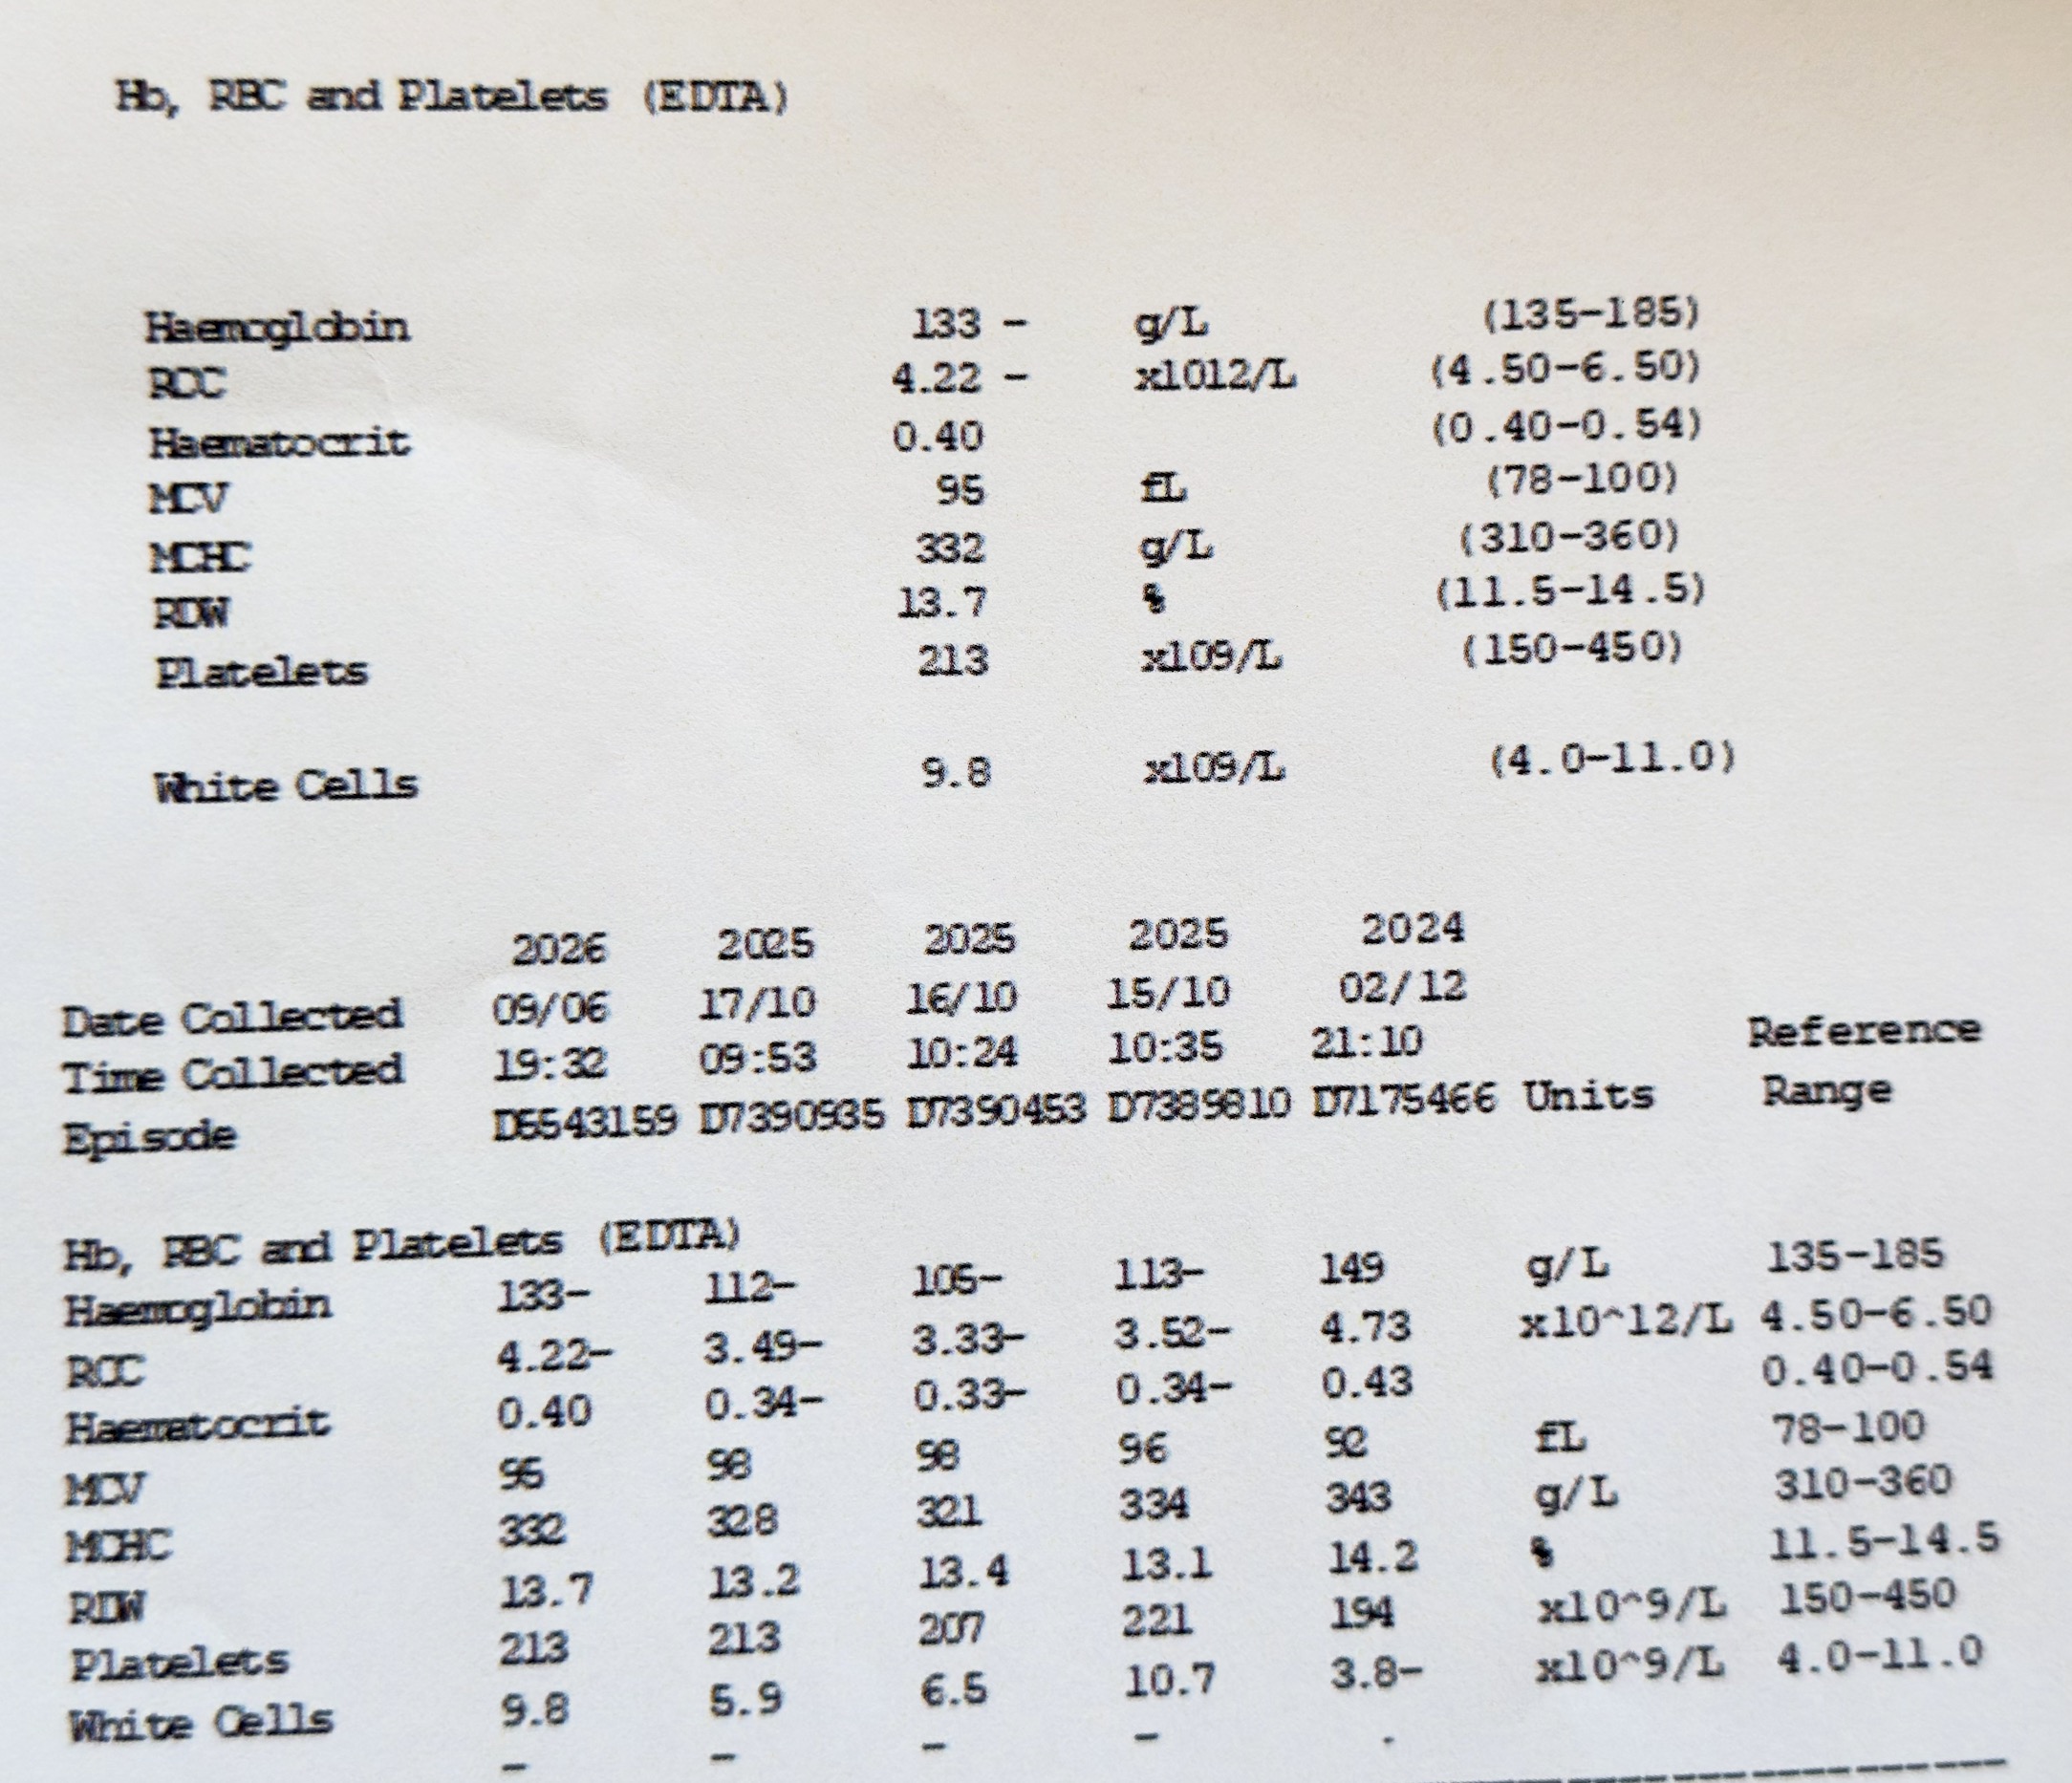
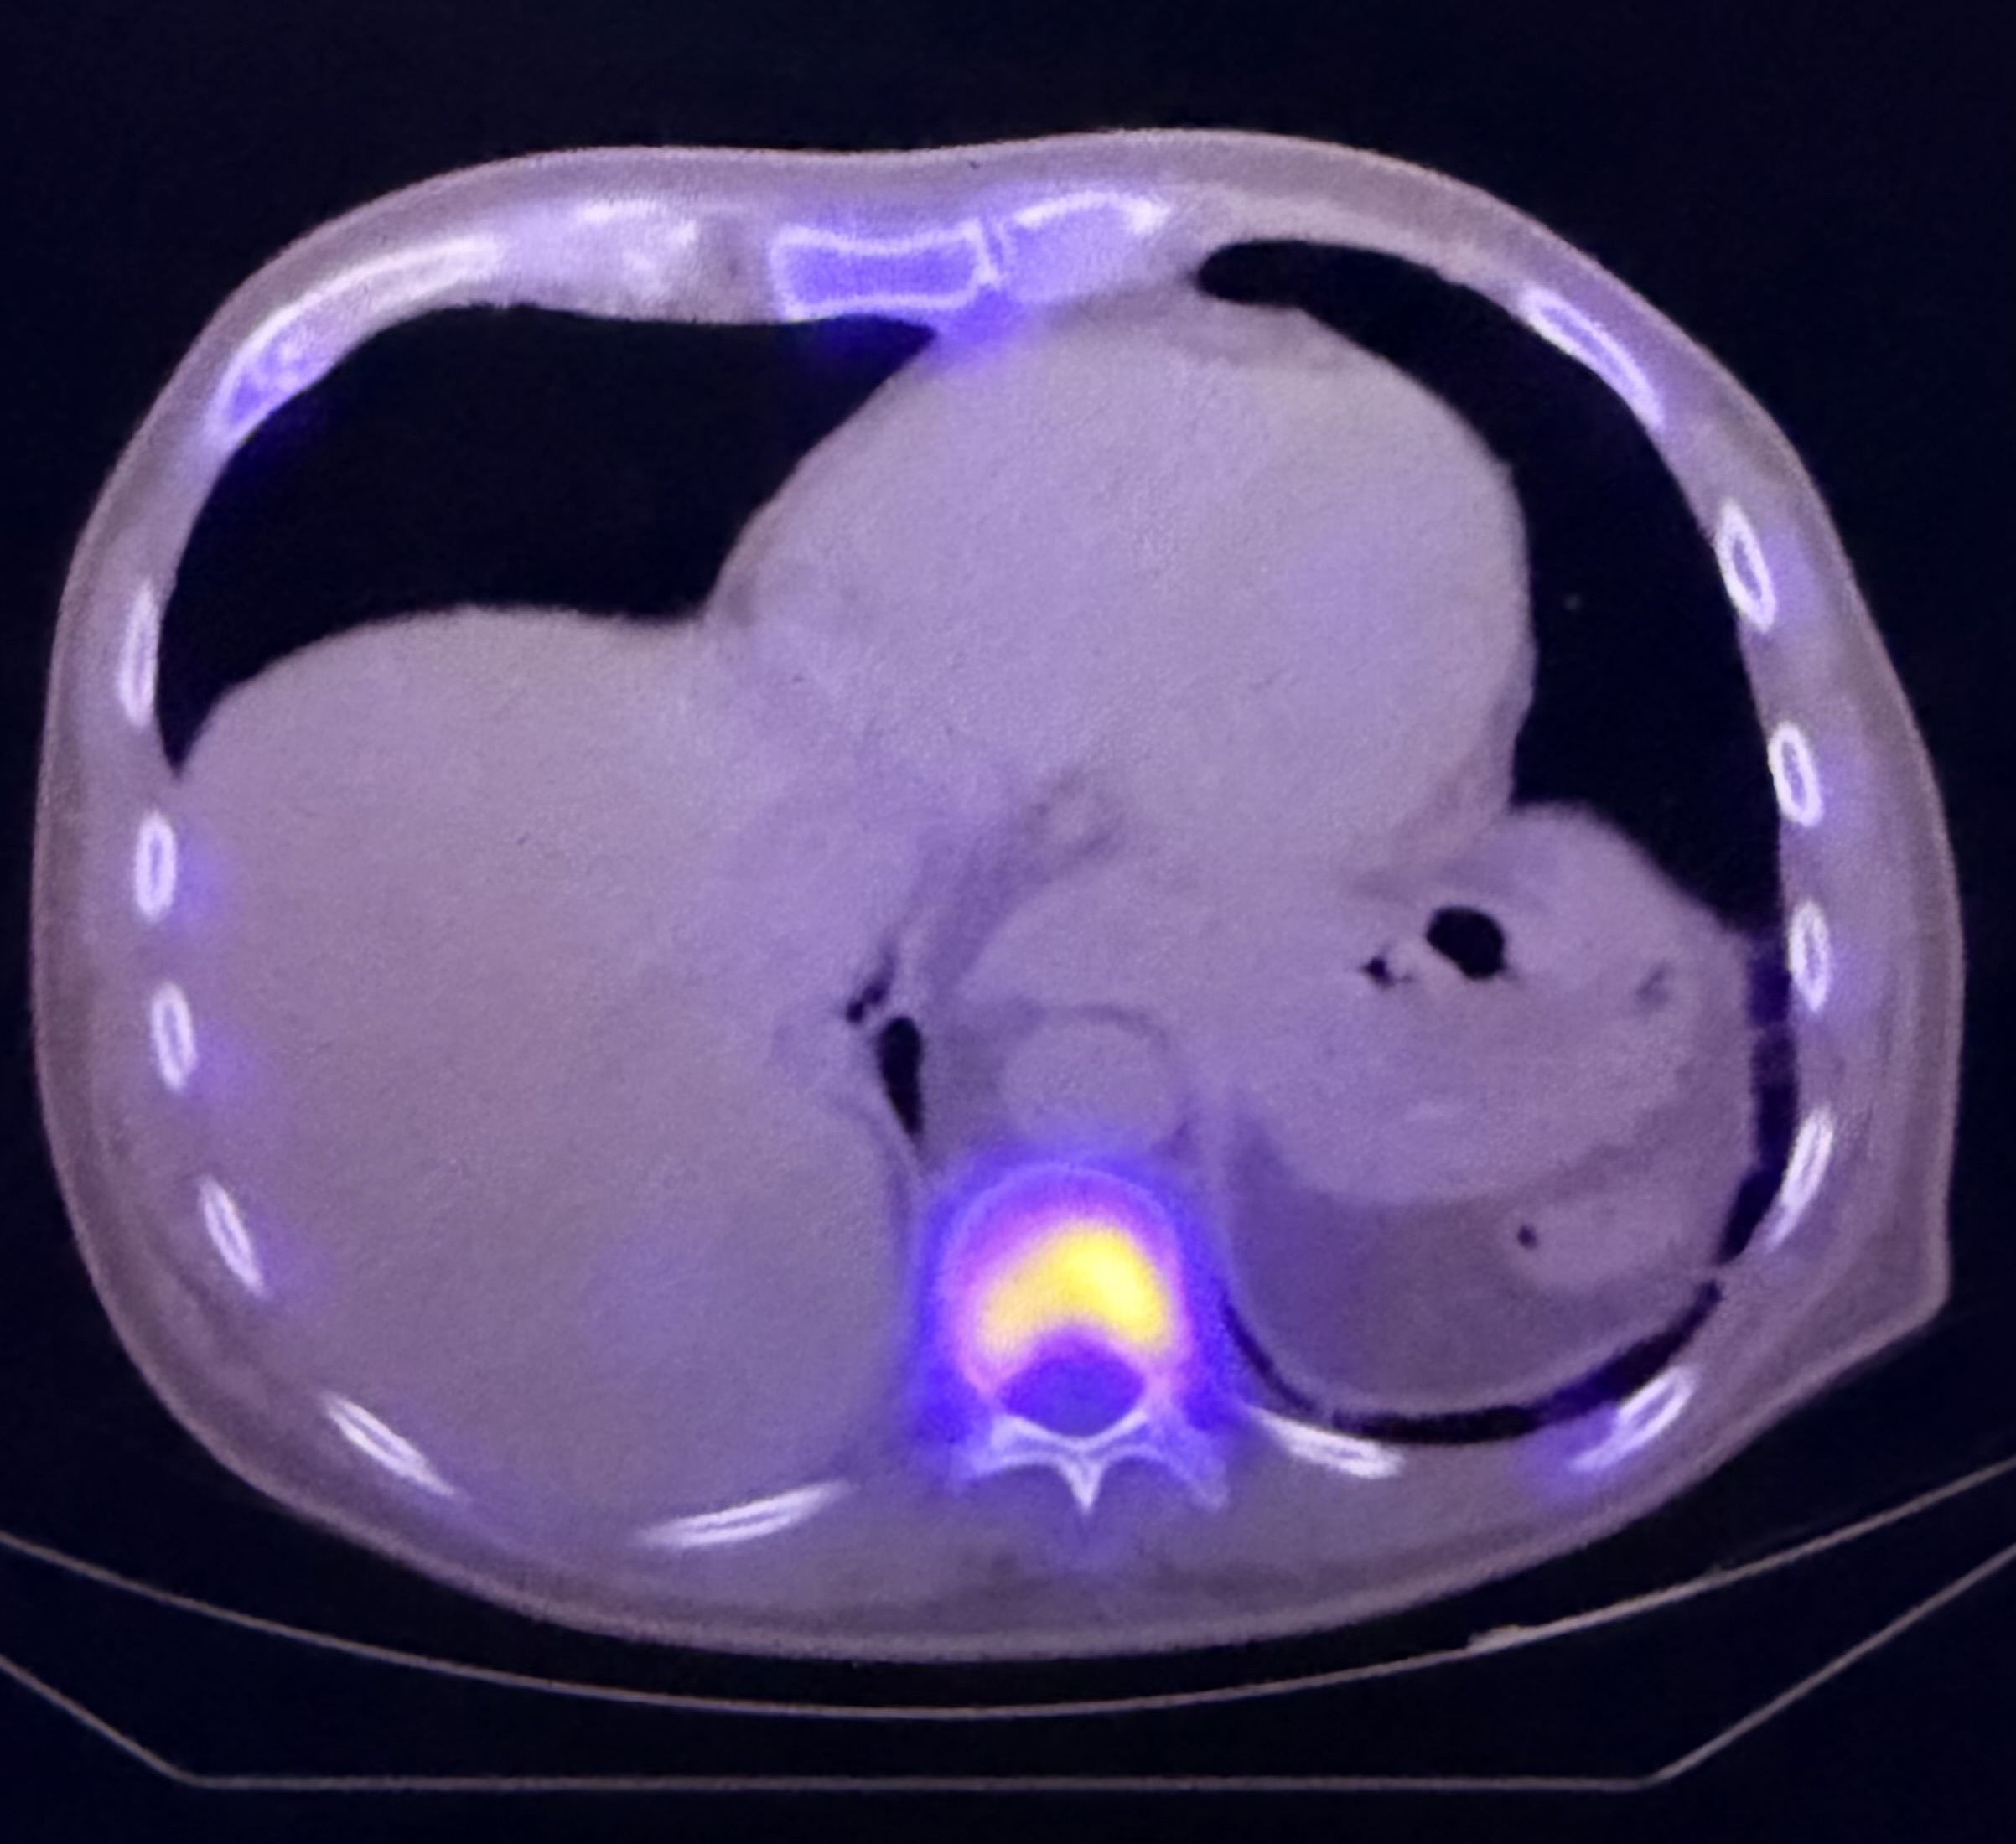
Diagnosis uses blood and urine protein tests, serum free light chains, bone marrow biopsy, cytogenetics/FISH, kidney and calcium tests, MRI, PET/CT or low-dose whole-body CT, and MRD testing in selected settings.
Treatment includes combinations of proteasome inhibitors, immunomodulatory drugs, steroids, monoclonal antibodies, stem cell transplant for eligible patients, maintenance therapy, CAR T-cell therapy, bispecific antibodies, radiation for focal pain, bone-strengthening therapy, and trials.
Condition-specific visual cues
Scans, pathology, and testing imagery
Stage 4 and metastatic disease
Advanced cancer context
Multiple myeloma is a marrow/plasma-cell cancer rather than a solid tumor staged 1-4; advanced disease can involve multiple bones, marrow failure, kidney injury, infections, high calcium, and extramedullary plasmacytomas.
Blood and urine protein studies, serum free light chains, bone marrow biopsy, cytogenetics/FISH, MRI, PET/CT or low-dose whole-body CT, kidney/calcium tests, and MRD testing may be used.
Relapsed/refractory myeloma is now a major immunotherapy setting, including CD38 antibodies, BCMA CAR T-cell therapy, BCMA and non-BCMA bispecific antibodies, and clinical trials for new targets.
Ask the oncology team whether stage 4 treatment is aiming for remission, long-term control, symptom relief, trial entry, or a sequence of several systemic treatments.
Treatment sequence
Where immunotherapy usually fits
Immunotherapy is often considered after surgery, radiation, chemotherapy, hormone therapy, or targeted therapy, especially when cancer is recurrent, metastatic, or hard to control. But that is not a fixed rule. In some cancers, immunotherapy is already used first-line, before surgery, after surgery to reduce recurrence risk, or early for biomarker-selected tumors. The right timing depends on the cancer type, stage, biomarkers, prior treatments, symptoms, urgency, performance status, and clinical trial availability.
This site separates current standard use from research-only use. Patients should ask their oncology team: Is immunotherapy approved for my exact cancer and stage, is it biomarker-dependent, and is there a trial that should be considered before or after conventional treatment?
Cost and access
Coverage changes frequently
Immunotherapy can be very expensive, especially CAR T-cell therapy, personalised vaccines, and newer checkpoint inhibitor combinations. This section is a current-status indicator only, not a guarantee of payment. A medicine may be approved but not funded, funded only for one cancer stage or biomarker group, or covered only after other treatments have been tried.
Always check the latest local formulary, insurer pre-authorisation rules, trial protocol, and the exact wording of the indication. Funding can change quickly when a new drug, biomarker group, line of therapy, or price agreement is approved.
The treating oncologist, cancer center pharmacist, clinical trials unit, social worker, or hospital financial navigator is usually the best source for current local access, insurer appeals, compassionate access, manufacturer programs, and whether a trial may cover the study drug.
United States
Government / public: Medicare/Medicaid may cover FDA-approved and medically accepted cancer immunotherapies when medical-necessity and site-of-care rules are met. Medicare has a national coverage determination for FDA-approved or compendia-supported autologous CAR T-cell therapy at REMS-enrolled facilities; non-FDA-approved CAR T is non-covered outside qualifying trial/routine-cost rules.
Private insurance: Private insurance may cover approved uses, but prior authorization, step therapy, network rules, specialty-center rules, copays, coinsurance, and denial appeals are common.
Australia
Government / public: PBS may subsidise listed immunotherapy medicines for specific cancer indications and restrictions; Medicare/MBS and public hospitals may cover services around treatment. Some cellular therapies are funded through specialised public hospital pathways rather than ordinary pharmacy dispensing.
Private insurance: Private health insurance may help with hospital and specialist costs, but unfunded cancer drugs or off-label immunotherapy may still be out-of-pocket unless specifically approved.
United Kingdom
Government / public: NHS access usually depends on NICE technology appraisal recommendations, Cancer Drugs Fund arrangements, or national commissioning rules for the exact medicine and indication.
Private insurance: Private insurance may cover approved oncology drugs if included in the policy and pre-authorised; off-label or trial-only use is often excluded.
Canada
Government / public: After Health Canada approval, public drug programs and cancer agencies decide reimbursement. CDA-AMC gives non-binding reimbursement recommendations; provinces and territories make final decisions, so access varies.
Private insurance: Private plans may cover some outpatient drugs, but many hospital-administered cancer drugs are handled through provincial cancer systems. Coverage is highly plan- and province-specific.
New Zealand
Government / public: Pharmac funding determines access for many medicines. A drug can be clinically useful or approved elsewhere but not publicly funded for a given New Zealand indication.
Private insurance: Private insurance or self-funding may help in selected cases, but high-cost immunotherapy can remain unaffordable without public funding or a trial.
European Union / EEA
Government / public: EMA marketing authorisation is not the same as reimbursement. Each country makes health-technology assessment, pricing, and reimbursement decisions through national systems.
Private insurance: Private cover varies widely by country and policy. Approved but not reimbursed indications may still require self-pay, compassionate access, or trial access.
Other countries
Government / public: Coverage varies greatly. Some countries fund only a limited set of immunotherapies; others require self-pay, charity access, manufacturer access programs, or referral to major cancer centers.
Private insurance: Insurance may cover approved cancer medicines, but high-cost CAR T, checkpoint inhibitors, vaccines, or off-label combinations often need pre-approval and may be excluded.
Approved and commonly used context
Current immunotherapy use
- BCMA-targeted CAR T-cell therapy and bispecific antibodies are important options for selected relapsed or refractory myeloma.
- Monoclonal antibodies such as CD38-targeting agents are major parts of current myeloma regimens.
- Treatment sequencing depends on prior drug classes, frailty, kidney function, cytogenetics, infections, and access to specialized centers.
What to watch next
Research direction
- Earlier-line CAR T, new targets such as GPRC5D and FcRH5, dual-target approaches, and outpatient bispecific treatment.
- Managing infections, low blood counts, cytokine-release syndrome, neurotoxicity, and relapse after BCMA therapy.
BCMA
CD38
GPRC5D
FcRH5
cytogenetics
MRD
triple-class exposed
Live trial radar
ClinicalTrials.gov links
Paper and source trail